Lupus Diagnosis Tests Understanding Key Evaluations
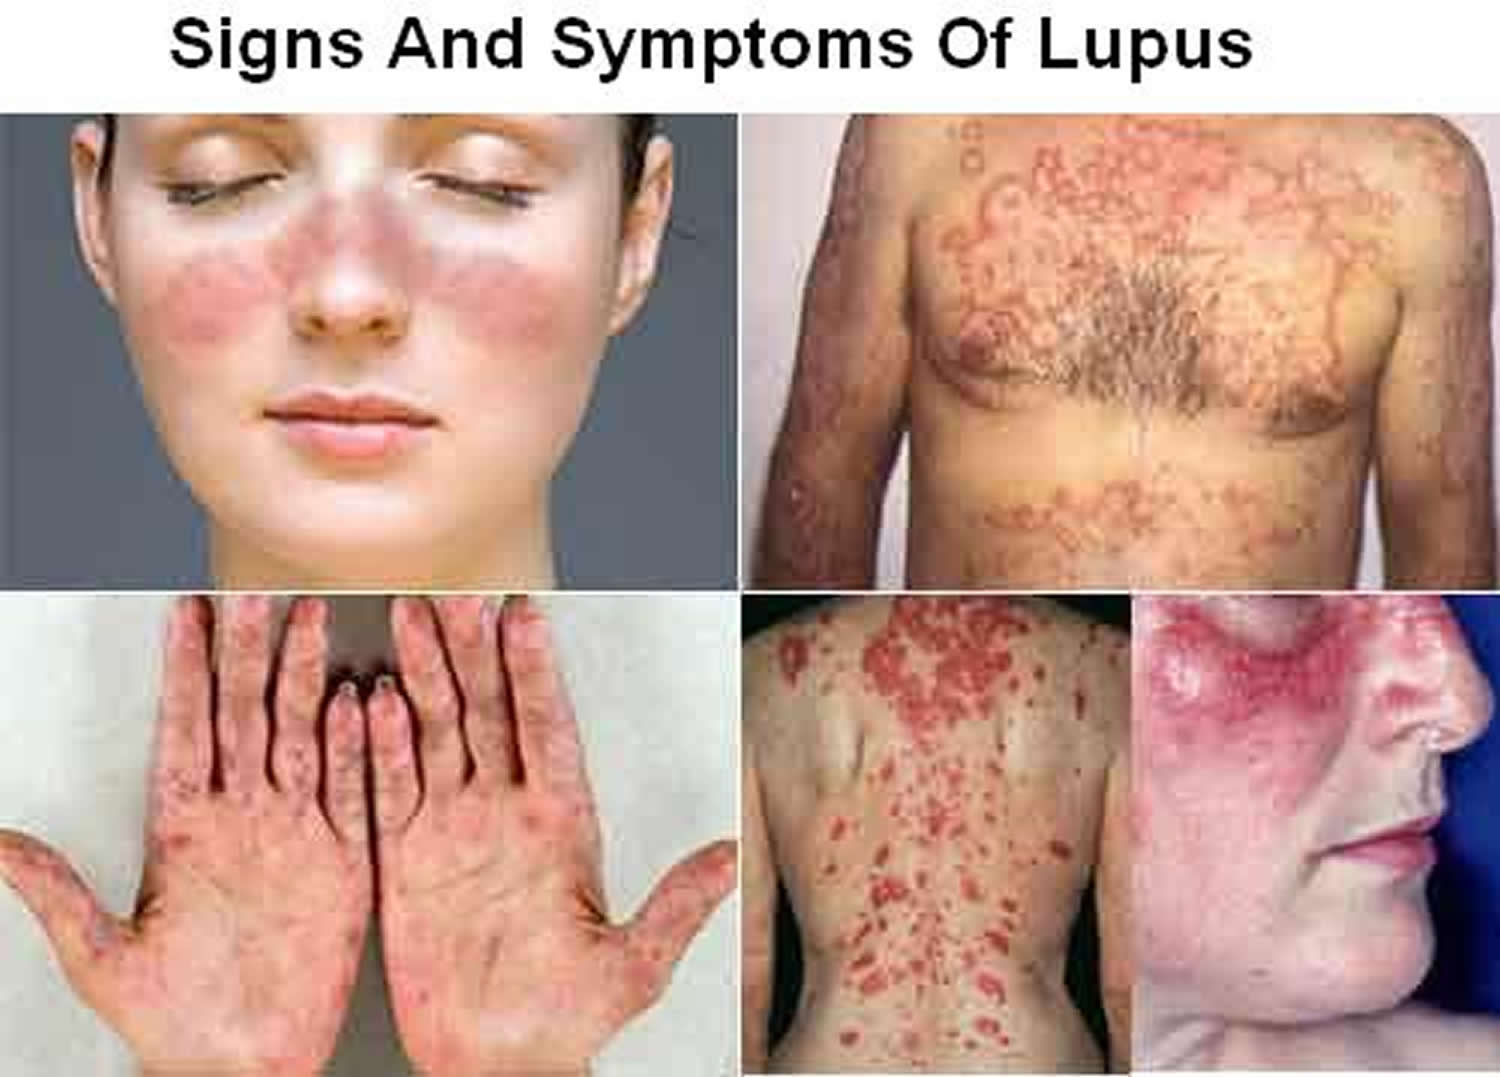
Table of Contents
- Types of Lupus Diagnosis Tests and Their Purpose
- Categories of Lupus Diagnosis Tests
- Step-by-Step Role of Diagnostic Tests in Lupus Confirmation
- Comparative Analysis: Laboratory Tests vs. Clinical Symptoms
- Blood-Based Biomarkers: Deep Dive into ANA and Beyond
- Role and Diagnostic Weight of Antinuclear Antibodies (ANA) and Subtypes
- Complement Proteins (C3, C4) and Their Role in Lupus Activity
- Emerging Biomarkers: Interferon Signatures and MicroRNAs
- Imaging and Procedural Tests in Lupus Diagnosis
- Role of Imaging Techniques in Lupus-Associated Organ Involvement
- Procedural Tests in Lupus Diagnosis: Indications, Risks, and Key Findings
- Clinical Scoring Systems and Diagnostic Criteria in Systemic Lupus Erythematosus
- Comparison of SLICC and ACR Diagnostic Criteria
- Integration of Test Results and Clinical Symptoms in Scoring Systems
- Role of the BILAG Index in Monitoring Disease Activity
- SLICC Criteria Patient Documentation Template
- Challenges and Limitations in Lupus Diagnosis
- Common Pitfalls in Lupus Diagnosis and Diagnostic Delays
- Demographic Variability in Test Accuracy and Diagnostic Approaches
- Diagnostic Challenges in Pediatric Lupus
Accurate lupus diagnosis remains a critical challenge in modern medicine due to its heterogeneous clinical presentation and overlapping symptoms with other autoimmune conditions. The diagnostic process relies on a meticulous integration of laboratory tests, imaging studies, and clinical criteria to distinguish lupus from mimics such as rheumatoid arthritis or fibromyalgia. Blood-based biomarkers, including antinuclear antibodies (ANA) and complement proteins, serve as foundational indicators, yet their interpretation demands nuance to avoid misdiagnosis or delayed treatment. Beyond serological assessments, advanced imaging and procedural tests—such as kidney biopsies or MRI scans—provide critical insights into organ-specific involvement, refining diagnostic precision. This exploration examines the evolving landscape of lupus diagnosis tests, from established methodologies to emerging biomarkers, while addressing the limitations that persist in clinical practice.
The complexity of lupus diagnosis underscores the necessity for a structured, evidence-based approach that balances sensitivity with specificity. Each diagnostic tool, whether a routine ANA screen or a high-risk kidney biopsy, plays a distinct role in confirming or ruling out lupus, particularly when symptoms are atypical or test results are ambiguous. Comparative analyses of diagnostic criteria—such as the SLICC and ACR frameworks—further illuminate how clinical scoring systems standardize decision-making, though demographic variations and pediatric considerations introduce additional layers of difficulty. By dissecting the strengths and pitfalls of current diagnostic protocols, this discussion aims to equip clinicians with actionable insights to improve early detection, reduce diagnostic delays, and optimize patient outcomes.
Types of Lupus Diagnosis Tests and Their Purpose
Systemic lupus erythematosus (SLE) diagnosis relies on a combination of clinical evaluation, laboratory tests, and diagnostic imaging to differentiate it from other autoimmune and inflammatory conditions. The American College of Rheumatology (ACR) and European League Against Rheumatism (EULAR) provide updated criteria emphasizing the integration of laboratory biomarkers, serological tests, and organ-specific assessments to confirm the presence of lupus. Below is a structured breakdown of diagnostic tests, their biological targets, and their role in the diagnostic workflow.Categories of Lupus Diagnosis Tests
Lupus diagnosis involves three primary categories of tests: serological blood tests, imaging studies, and tissue biopsies. Each category serves distinct purposes—ranging from detecting autoimmune activity to assessing organ involvement—and contributes to a composite diagnostic picture.Serological blood tests are the cornerstone of lupus diagnosis, identifying autoantibodies and inflammatory markers. Imaging studies (e.g., ultrasound, MRI) evaluate organ damage, while biopsies provide histological confirmation for organ-specific manifestations. Below is a comparative table summarizing these tests:
| Test Name | Purpose | Biological Markers Detected | Limitations |
|---|---|---|---|
| Antinuclear Antibody (ANA) | Screening for autoimmune activity; high sensitivity but low specificity for lupus. | Autoantibodies targeting nuclear antigens (e.g., histones, dsDNA, Sm, RNP). | Positive in 5–15% of healthy individuals; false positives in other autoimmune diseases (e.g., rheumatoid arthritis, Sjögren’s syndrome). |
| Anti-double-stranded DNA (anti-dsDNA) | Highly specific for lupus; correlates with disease activity, particularly renal involvement. | Autoantibodies against double-stranded DNA. | False negatives in early disease or during remission; less sensitive than ANA. |
| Complement Levels (C3, C4, CH50) | Indicates immune complex deposition and disease flares; low levels suggest active lupus. | Decreased C3/C4 due to consumption in immune complex-mediated inflammation. | Non-specific; can be low in other infections or liver diseases. |
| Anti-Smith (anti-Sm) Antibodies | Highly specific for SLE; supports diagnosis when positive. | Autoantibodies against Sm nuclear antigen. | Low sensitivity (~30% of lupus patients); rare in other conditions. |
| Anti-Ribonucleoprotein (anti-RNP) | Associated with lupus and mixed connective tissue disease (MCTD). | Autoantibodies against U1-RNP. | Non-specific; may appear in other autoimmune diseases. |
| Erythrocyte Sedimentation Rate (ESR) / C-Reactive Protein (CRP) | Non-specific markers of inflammation; elevated in active lupus. | ESR measures red blood cell aggregation; CRP reflects acute-phase response. | CRP often normal in lupus (unlike bacterial infections); ESR less specific. |
| Urinalysis / Proteinuria | Detects lupus nephritis via proteinuria, hematuria, or cellular casts. | Proteinuria (>0.5 g/24h), red blood cell casts, or active sediment. | Non-specific; requires renal biopsy for definitive diagnosis. |
| Chest X-ray / High-Resolution CT (HRCT) | Evaluates pleuritis or interstitial lung disease in lupus. | Pleural effusions, ground-glass opacities, or lymphadenopathy. | False negatives in early or mild pulmonary involvement. |
| Skin Biopsy (Direct Immunofluorescence) | Confirms lupus-specific skin changes (e.g., malar rash) via IgG/IgM deposition. | Deposits of IgG, IgM, or C3 at the dermo-epidermal junction. | Not required for diagnosis but useful in atypical presentations. |
| Renal Biopsy | Gold standard for diagnosing lupus nephritis (Class I–VI). | Glomerulonephritis patterns (e.g., wire-loop lesions, immune complex deposits). | Invasive; risks include bleeding or infection. |
Step-by-Step Role of Diagnostic Tests in Lupus Confirmation
The diagnostic process follows a tiered approach, beginning with broad screening tests and progressing to specialized assays based on clinical suspicion. Below is the sequential contribution of each test type:1. Initial Screening with ANA
2. Lupus-Specific Antibody Testing (anti-dsDNA, anti-Sm, anti-RNP)
3. Complement and Inflammatory Markers (C3, C4, ESR, CRP)
4. Organ-Specific Testing (Urinalysis, Imaging, Biopsies)
Comparative Analysis: Laboratory Tests vs. Clinical Symptoms
Laboratory biomarkers and clinical manifestations of lupus often correlate imperfectly, requiring integration for accurate diagnosis. Below are key takeaways from comparative studies:1. ANA Sensitivity vs. Clinical Presentation:
ANA is highly sensitive but lacks specificity; ~5% of healthy individuals test positive. Clinical relevance: A positive ANA in a patient with arthralgias, malar rash, or photosensitivity strengthens suspicion, whereas an isolated positive ANA in an asymptomatic patient may represent a benign finding. 2. Anti-dsDNA and Disease Activity:
Correlation with renal lupus: Anti-dsDNA titers often rise during flares, particularly nephritis. Limitations: False negatives occur in early disease or remission; some patients with severe lupus may lack detectable anti-dsDNA. 3. Complement Levels and Prognosis:
Low C3/C4: Indicates active immune complex deposition (e.g., nephritis, vasculitis). Normalization: Suggests treatment response but does not rule out subclinical disease. <
Blood-Based Biomarkers: Deep Dive into ANA and Beyond
The diagnosis of systemic lupus erythematosus (SLE) relies heavily on blood-based biomarkers, with antinuclear antibodies (ANA) serving as a cornerstone due to their high sensitivity. However, their specificity varies significantly depending on the antibody subtype, necessitating a nuanced interpretation alongside clinical correlation. Beyond ANA, emerging biomarkers—such as interferon signatures and microRNAs—hold promise for refining diagnostic accuracy, though their integration into standard practice remains limited by validation challenges. This section explores the diagnostic weight of ANA and its subtypes, the role of complement proteins in disease activity, and the potential of novel biomarkers, while addressing common pitfalls in test interpretation.
Role and Diagnostic Weight of Antinuclear Antibodies (ANA) and Subtypes
ANA are autoantibodies targeting nuclear antigens, detectable in 95–98% of SLE patients but also present in other autoimmune diseases, infections, and even healthy individuals (up to 15% in the general population). Their diagnostic utility stems from high sensitivity, though low specificity requires confirmation via additional tests. The American College of Rheumatology (ACR) and European League Against Rheumatism (EULAR) classify ANA positivity (≥1:80 titer by immunofluorescence) as a supportive criterion for SLE, not a definitive marker.The following table summarizes key ANA subtypes, their prevalence in lupus, specificity, and clinical relevance:
Key Interpretation Guidelines:
Antibody Type Prevalence in Lupus Specificity Clinical Relevance Anti-Smith (anti-Smith/RNP) 20–30% High (95–99%)
- Highly specific for SLE; rarely found in other autoimmune diseases.
- Strongly associated with renal and neurological involvement.
- Presence supports classification criteria but does not correlate with disease severity.
Anti-dsDNA 30–70% Moderate (80–90%)
- Strongly linked to lupus nephritis and disease flares.
- Titer fluctuations often precede clinical exacerbations.
- False positives in infections (e.g., malaria, EBV) and other CTDs (e.g., rheumatoid arthritis).
Anti-RNP (Ribonucleoprotein) 30–50% Low (50–60%)
- Common in SLE but also present in mixed connective tissue disease (MCTD).
- May indicate milder disease or overlap syndromes.
- Less predictive of organ damage compared to anti-Smith or anti-dsDNA.
Anti-histone 50–70% Low (30–40%)
- Strongly associated with drug-induced lupus (e.g., procainamide, hydralazine).
- Less specific for idiopathic SLE; may resolve with drug cessation.
Anti-SSA/Ro and Anti-SSB/La 20–30% Moderate (70–80%)
- Linked to neonatal lupus (congenital heart block) and Sjögren’s syndrome.
- May persist in asymptomatic carriers.
- Less specific for SLE but supports overlap diagnoses.
ANA positivity alone is insufficient for SLE diagnosis; subtype testing (e.g., anti-dsDNA, anti-Smith) is critical for specificity. High-titer ANA (≥1:320) increases suspicion but does not replace clinical evaluation. Negative ANA does not rule out SLE, particularly in early or atypical cases (e.g., pediatric or African-American patients, where prevalence may be lower). Complement Proteins (C3, C4) and Their Role in Lupus Activity
Complement proteins C3 and C4 are acute-phase reactants that decline during active lupus due to immune complex deposition and consumption. Their measurement provides objective evidence of disease flare, independent of ANA status.- Mechanism of Depletion:
In SLE, immune complexes (e.g., anti-dsDNA/DNA) activate the classical complement pathway, leading to:
- Accelerated consumption of C4 (early pathway marker).
- Subsequent depletion of C3 (common pathway marker).
- Reduced opsonization and phagocytosis, exacerbating inflammation.
Clinical Interpretation: Low C3/C4 levels correlate with:
- Active lupus nephritis or vasculitis.
- Increased risk of flares (particularly in anti-dsDNA-positive patients).
Normal or elevated levels suggest:
- Inactive disease or treatment response (e.g., corticosteroids, immunosuppressants).
- Possible genetic complement deficiencies (e.g., C2, C4 null alleles), which may predispose to SLE.
Transient elevations may occur during infections or with acute-phase reactants (e.g., CRP, fibrinogen), requiring clinical correlation. Limitations: False negatives in early disease or with complement-regulatory protein polymorphisms (e.g., CFHR1/3). False positives in liver disease, pregnancy, or acute infections (e.g., hepatitis, sepsis). Not specific for SLE; low levels also seen in other autoimmune diseases (e.g., vasculitis, rheumatoid arthritis). Emerging Biomarkers: Interferon Signatures and MicroRNAs
While ANA and complement tests remain standard, novel biomarkers offer potential for earlier diagnosis and personalized monitoring. Two promising categories include:1. Interferon (IFN) Signatures:
Mechanism: SLE is characterized by type I IFN (IFN-α/β) overproduction, detectable via gene expression profiling (e.g., IFN signature score). Advantages:
- Highly specific for SLE (sensitivity ~80%, specificity ~90%).
Predicts disease activity and response to IFN-blocking therapies (e.g., anifrolumab). May identify seronegative lupus (ANA-negative cases). Barriers to Adoption:
- Requires whole-blood RNA sequencing, limiting accessibility.
Standardization across platforms is ongoing. Cost and technical complexity hinder routine use. 2. MicroRNAs (miRNAs):
Mechanism: Small non-coding RNAs (e.g., miR-146a, miR-155) regulate immune responses and are dysregulated in SLE. Advantages:
- Stable in serum/plasma, enabling non-invasive monitoring.
Potential to distinguish SLE from other autoimmune diseases (e.g., miR-146a elevated in SLE vs. rheumatoid arthritis). Correlates with disease activity and organ involvement (e.g., miR-21 linked to lupus nephritis). Barriers to Adoption Imaging and Procedural Tests in Lupus Diagnosis
Imaging and procedural tests play a critical role in assessing lupus-related organ involvement, particularly when clinical symptoms suggest systemic complications such as nephritis, neuropsychiatric lupus, or pulmonary disease. While serological biomarkers like ANA and anti-dsDNA guide diagnosis, imaging techniques and invasive procedures provide direct evidence of tissue damage, inflammation, or immune complex deposition. These modalities are essential for staging disease severity, monitoring progression, and tailoring therapeutic interventions. Below, the focus is on the application of imaging modalities and procedural tests, their indications, and the pathological findings that inform lupus management.
Role of Imaging Techniques in Lupus-Associated Organ Involvement
Imaging studies are instrumental in identifying lupus-related complications in high-risk organs, including the kidneys, central nervous system (CNS), lungs, and cardiovascular system. The choice of modality depends on the suspected organ involvement, availability of resources, and patient-specific factors such as contrast allergies or renal function.Kidney Involvement (Lupus Nephritis)
Magnetic resonance imaging (MRI) with contrast enhancement is increasingly used to evaluate lupus nephritis (LN) due to its superior soft-tissue resolution and lack of ionizing radiation. Key findings include:
Diffuse cortical thickening or focal lesions suggestive of inflammation. Restricted diffusion on diffusion-weighted imaging (DWI), indicating acute cellular injury. Contrast enhancement patterns correlating with active inflammation (e.g., cortical hyperenhancement in Class III/IV LN). Computed tomography (CT) scans are less preferred due to radiation exposure but may reveal:
Perinephric stranding or hydronephrosis secondary to ureteral obstruction from LN. Calcifications in chronic LN, though these are non-specific. Ultrasound is primarily used for screening due to its accessibility and lack of radiation, detecting:
Increased echogenicity of the renal parenchyma. Loss of corticomedullary differentiation, often correlating with active nephritis. Central Nerviatric System (CNS) Involvement
MRI remains the gold standard for evaluating neuropsychiatric lupus (NPSLE), with T2-weighted/FLAIR sequences identifying:
White matter lesions (e.g., in multiple sclerosis-like presentations). Cortical or subcortical infarcts from vasculitis or thrombosis. Transverse myelitis or cerebral atrophy in chronic cases. Contrast-enhanced MRI may reveal meningeal enhancement or vasculitic changes in active disease.Pulmonary Complications
High-resolution CT (HRCT) is critical for diagnosing lupus-related lung disease, including:
Ground-glass opacities (GGOs) or consolidation in lupus pneumonitis. Pleural effusions (often exudative) or interstitial lung disease (ILD) patterns. Pulmonary hypertension via echocardiogram or right-heart catheterization, though imaging may show enlarged pulmonary arteries or right ventricular strain. Cardiovascular and Musculoskeletal Involvement
Echocardiography assesses pericardial effusions, valvular vegetations (Libman-Sacks endocarditis), or diastolic dysfunction. Doppler ultrasound of peripheral joints evaluates synovitis or tenosynovitis in lupus arthritis. Dual-energy X-ray absorptiometry (DEXA) screens for osteoporosis, common in long-term glucocorticoid use. When Imaging Is Requested
Imaging is typically warranted when:
Clinical symptoms (e.g., hematuria, proteinuria, seizures, dyspnea) suggest organ-specific involvement. Serological markers (e.g., elevated anti-dsDNA, low C3/C4) indicate active disease but lack specificity. Treatment response is suboptimal, and alternative diagnoses (e.g., infection, malignancy) must be excluded. Pre-procedural assessment is required (e.g., CT angiography before biopsy to map vascular anatomy). Procedural Tests in Lupus Diagnosis: Indications, Risks, and Key Findings
Procedural tests provide definitive diagnostic evidence in lupus, particularly for organ-specific complications. Below is a structured overview of common procedures, their indications, associated risks, and pathological findings.
Procedure Name Indications Risks Key Findings Kidney Biopsy
- Persistent proteinuria (>0.5 g/day) or nephrotic syndrome.
- Active urinary sediment (e.g., cellular casts, dysmorphic RBCs).
- Rising creatinine with suspected LN despite immunosuppressive therapy.
- Differentiating LN from other glomerulonephritides (e.g., IgA nephropathy).
- Bleeding (hematuria, perirenal hematoma; ~5–10% risk).
- Arterial hypertension or hypotension during procedure.
- Infection (rare, <1%).
- Post-biopsy pain or transient hematuria (common).
- Light microscopy:
- Endocapillary proliferation (Class III/IV LN).
- Wire-loop lesions (thickened glomerular basement membranes).
- Fibrous crescents (chronic LN).
- Immunofluorescence:
- Full-house pattern (IgG, IgA, IgM, C3, C1q deposits).
- Subendothelial or mesangial immune complex deposition.
- Electron microscopy:
- Subendothelial electron-dense deposits.
- Mesangial interposition (Class IV LN).
Synovial Fluid Analysis
- Acute arthritis or synovitis unresponsive to NSAIDs.
- Suspected septic arthritis (to rule out infection).
- Minimal (e.g., pain, bleeding at aspiration site).
- Infection risk (<1% with aseptic technique).
- Non-inflammatory: <500 cells/μL (unlikely in active lupus arthritis).
- Inflammatory: 2,000–50,000 cells/μL (predominantly neutrophils in septic arthritis; lymphocytes in lupus).
- Negative Gram stain/culture (rules out infection).
- Rheumatoid factor or anti-CCP negative (distinguishes from rheumatoid arthritis).
Lumbar Puncture (LP)
- New-onset headache, seizures, or focal neurological deficits (NPSLE).
- Suspected aseptic meningitis or cerebral vasculitis.
- Post-lumbar puncture headache (~20–30%).
- Herniation risk in patients with mass lesions (rare).
- Infection or bleeding (<1%).
- Lymphocytic pleocytosis (5–50 cells/μL, often <100).
- Elevated protein (>50 mg/dL) or low glucose (<40 mg/dL).
- Negative Gram stain/Viral PCR (rules out infection).
- Oligoclonal bands (non-specific but may suggest CNS inflammation).
Bronchoalveolar Lavage (BAL)
- Interstitial lung disease or unexplained pulmonary infiltrates.
- Suspected
Example Integration:
Clinical Scoring Systems and Diagnostic Criteria in Systemic Lupus Erythematosus
Systemic lupus erythematosus (SLE) diagnosis relies on a combination of clinical manifestations, laboratory findings, and standardized criteria to ensure accuracy and consistency. Clinical scoring systems, such as those developed by the Systemic Lupus International Collaborating Clinics (SLICC) and the American College of Rheumatology (ACR), provide structured frameworks for classifying lupus and distinguishing it from other autoimmune diseases. These criteria integrate serological biomarkers, organ-specific damage, and symptomology to facilitate early detection, treatment planning, and research standardization. Below, a comparative analysis of SLICC and ACR criteria is presented, followed by an exploration of their integration with diagnostic tests and the role of the British Isles Lupus Assessment Group (BILAG) index in longitudinal monitoring.
Comparison of SLICC and ACR Diagnostic Criteria
The SLICC 2012 criteria and the ACR/EULAR 2019 criteria represent the most widely adopted frameworks for SLE classification, each offering distinct advantages in sensitivity, specificity, and clinical applicability. Sensitivity refers to a criterion’s ability to correctly identify true lupus cases, while specificity measures its accuracy in excluding non-lupus conditions. Below is a comparative table summarizing key differences:
Key Insight: The ACR/EULAR 2019 criteria improve sensitivity for early lupus by incorporating weighted scores, while SLICC remains favored for its simplicity in routine practice. Both require ANA positivity (≥1:80 titer) as a foundational criterion, though SLICC permits diagnosis without ANA if biopsy-proven lupus nephritis is present.
Feature SLICC 2012 Criteria ACR/EULAR 2019 Criteria Primary Focus Combines clinical and immunologic criteria with emphasis on organ damage and ANA positivity. Updates ACR 1997 criteria with weighted scoring (e.g., ANA positivity contributes 2 points, while malar rash contributes 4). Sensitivity ~90% (higher than ACR 1997 but slightly lower than ACR/EULAR 2019). ~96% (improved sensitivity for early or mild lupus cases). Specificity ~85% (balanced for clinical use but may overdiagnose in some populations). ~80% (slightly lower due to broader inclusion of mild symptoms). Diagnostic Threshold 4 out of 17 criteria (ANA positivity + ≥1 clinical + ≥1 immunologic OR biopsy-proven lupus nephritis). ≥10 points from weighted clinical/immunologic items (ANA positivity alone = 2 points). Immunologic Criteria Anti-dsDNA, anti-Smith, antiphospholipid antibodies, low complement (C3/C4), or direct Coombs test. Anti-dsDNA, anti-Smith, antiphospholipid antibodies, low complement, or high anti-Ro/La (weighted differently). Clinical Utility Simpler for clinical practice; emphasizes organ damage (e.g., lupus nephritis). More granular scoring allows detection of early or atypical lupus; better for research. Adoption in Guidelines Preferred in Europe and many clinical settings for its practicality. Endorsed by ACR/EULAR; increasingly used in global studies.
Integration of Test Results and Clinical Symptoms in Scoring Systems
Scoring systems synthesize laboratory biomarkers, organ-specific damage, and symptoms to assign an SLE diagnosis. The process involves:
1. Serological Validation: ANA positivity (≥1:80) is mandatory in both SLICC and ACR/EULAR criteria. Additional immunologic tests (e.g., anti-dsDNA, anti-Smith) provide supporting evidence.
2. Clinical Manifestations: Symptoms like malar rash, arthritis, or serositis contribute to the total score. For example:
- SLICC: Requires ≥1 clinical criterion (e.g., oral ulcers, non-scarring alopecia) and ≥1 immunologic criterion (or lupus nephritis biopsy).
- ACR/EULAR: Assigns points (e.g., malar rash = 4, arthritis = 2) to reach the ≥10-point threshold.
3. Organ Damage: Chronic damage (e.g., avascular necrosis, chronic renal failure) may be captured under SLICC’s "persistent proteinuria" or ACR/EULAR’s "renal disorder" categories.Thresholds for Diagnosis:
For SLICC 2012:
- ANA positivity (≥1:80) + ≥1 clinical criterion + ≥1 immunologic criterion, OR
- ANA positivity (≥1:80) + biopsy-proven lupus nephritis.
For ACR/EULAR 2019:
- ≥10 points from weighted clinical/immunologic items (e.g., ANA = 2, anti-dsDNA = 4, lupus nephritis = 8).
A patient with:
- Positive ANA (1:160),
- Anti-dsDNA antibodies,
- Malar rash,
- Arthritis,
- Low C3/C4 levels,
would meet SLICC criteria (ANA + clinical + immunologic) and ACR/EULAR criteria (≥10 points: ANA=2, rash=4, arthritis=2, anti-dsDNA=4, low complement=2).
Role of the BILAG Index in Monitoring Disease Activity
The British Isles Lupus Assessment Group (BILAG) index is a dynamic tool for assessing disease activity across nine organ systems (e.g., mucocutaneous, musculoskeletal, renal). Unlike static diagnostic criteria, BILAG evaluates current symptoms and laboratory changes to guide treatment adjustments. It classifies activity into four grades:
- A (Active): Severe, life-threatening involvement (e.g., lupus nephritis with creatinine >3.0 mg/dL).
- B (Moderate): Significant but non-life-threatening (e.g., arthritis with joint deformity).
- C (Mild): Non-specific symptoms (e.g., fatigue, mild rash).
- D (Inactive): No activity in that system.
Application in Clinical Practice:
- Baseline Assessment: At diagnosis, BILAG identifies dominant organ systems (e.g., renal A, musculoskeletal B).
- Serial Monitoring: Changes in BILAG grades (e.g., from B to A in renal system) trigger escalation of immunosuppressants (e.g., mycophenolate mofetil for nephritis).
- Treatment Response: Improvement to grade D or C may allow tapering of steroids or antimalarials.
Example Workflow:
A patient with BILAG renal A (active nephritis) and BILAG musculoskeletal B (arthritis) may require:
- Induction therapy (e.g., IV cyclophosphamide) for renal A.
- Maintenance therapy (e.g., hydroxychloroquine + low-dose prednisone) for musculoskeletal B.
After 6 months, if renal activity improves to BILAG renal B, the regimen may shift to azathioprine + tapering steroids.
SLICC Criteria Patient Documentation Template
Standardized documentation ensures consistency in applying SLICC criteria. Below is a template for recording patient data:
Section Details SLICC Criteria Met? Immunologic Criteria (Require ≥1) Anti-nuclear antibodies (ANA) titer □ ≥1:80 (Yes/No) Anti-dsDNA antibodies
Challenges and Limitations in Lupus Diagnosis
Systemic lupus erythematosus (SLE) presents a complex diagnostic landscape due to its heterogeneous clinical manifestations, overlapping features with other autoimmune and non-autoimmune conditions, and variability in biomarker expression. Accurate diagnosis hinges on integrating laboratory findings, clinical presentation, and exclusion of mimicking disorders, yet pitfalls such as non-specific symptoms, demographic disparities in test performance, and age-related differences in biomarker profiles introduce significant challenges. These limitations often lead to diagnostic delays, misclassification, or underdiagnosis, particularly in high-risk populations. Addressing these challenges requires a structured approach to interpretation, awareness of test limitations, and adherence to evolving diagnostic criteria tailored to diverse patient groups.
Common Pitfalls in Lupus Diagnosis and Diagnostic Delays
The non-specific nature of lupus symptoms—such as fatigue, arthralgia, and fever—frequently overlaps with conditions like fibromyalgia, rheumatoid arthritis (RA), or even viral infections, complicating initial assessments. Misinterpretation of test results, particularly false negatives in serological markers or transient elevations in inflammatory indices, further obscures diagnosis. Below are key pitfalls contributing to delays:
- Symptom Overlap with Other Autoimmune Diseases Lupus shares clinical and laboratory features with rheumatoid arthritis (e.g., arthralgia, positive rheumatoid factor), Sjögren’s syndrome (e.g., sicca symptoms, anti-SSA/SSB antibodies), and antiphospholipid syndrome (e.g., thrombotic events, prolonged aPTT). For instance, up to 30% of patients with SLE may initially be misdiagnosed with RA due to symmetric arthritis and elevated ESR, leading to inappropriate treatment with disease-modifying antirheumatic drugs (DMARDs) that may exacerbate lupus activity.
Example: A 2019 study in Arthritis & Rheumatology found that 28% of SLE patients were initially diagnosed with another autoimmune disease, with RA being the most common misdiagnosis.- False-Negative or Non-Specific Serological Results The absence of anti-dsDNA antibodies or low-titer ANA does not exclude lupus, as 15–20% of SLE patients may test negative for these markers, particularly in early disease or during remission. Conversely, positive ANA (present in ~10% of healthy individuals) lacks specificity, leading to overdiagnosis in asymptomatic patients. Transient elevations in CRP or ESR may also mimic infection or other inflammatory conditions, delaying lupus evaluation.
Key Insight: The 1997 American College of Rheumatology (ACR) criteria relied heavily on serological markers, but modern revisions (e.g., 2019 EULAR/ACR criteria) incorporate clinical features to mitigate false exclusions.- Inconsistent Biomarker Presentation Across Disease Stages Biomarkers like complement levels (C3/C4) and anti-dsDNA fluctuate with disease activity, creating challenges in longitudinal assessment. A single negative anti-dsDNA test does not rule out lupus, as titers may normalize during remission despite persistent clinical symptoms. Similarly, hypocomplementemia may be absent in 20–30% of SLE patients, particularly those with mild or non-renal disease.
Statistical Note: A 2020 Lupus Science & Medicine analysis reported that only 50% of SLE patients exhibit all four classic biomarkers (ANA, anti-dsDNA, low C3/C4, and thrombocytopenia) at diagnosis.- Delayed Recognition of Atypical Presentations Lupus can manifest as lupus nephritis without systemic symptoms, neuropsychiatric lupus (NPSLE) as the sole presentation, or isolated cutaneous disease (e.g., subacute cutaneous lupus). For example, NPSLE accounts for 10–20% of initial lupus presentations but is often attributed to psychiatric disorders or migraines, leading to delays of 1–5 years before correct diagnosis.
Clinical Red Flag: Persistent headaches with cognitive dysfunction, seizures without structural lesions, or chorea in young adults should prompt evaluation for NPSLE.Demographic Variability in Test Accuracy and Diagnostic Approaches
Lupus exhibits significant heterogeneity across racial, ethnic, and gender groups, influencing the sensitivity and specificity of diagnostic tests. These disparities stem from genetic predispositions, environmental exposures, and differences in disease severity. Below are key demographic considerations:
- Racial and Ethnic Disparities in Biomarker Expression African Americans and Hispanics have a 2–3 times higher prevalence of SLE compared to Caucasians, yet their biomarker profiles may differ. For example:
Group Anti-dsDNA Prevalence ANA Sensitivity Lupus Nephritis Risk African American ~70% ~95% ~50% Caucasian ~50% ~85% ~30% Asian ~40% ~80% ~20% Implication: Lower anti-dsDNA positivity in Asians may lead to underdiagnosis if clinicians rely solely on serological criteria.- Gender-Specific Challenges While SLE is 9 times more common in women, male patients often present with more severe disease (e.g., higher rates of nephritis, cardiovascular complications) and atypical symptoms (e.g., pulmonary involvement, serositis). Male SLE patients are also less likely to have positive ANA (sensitivity ~70% vs. ~90% in females), increasing the risk of misdiagnosis as RA or vasculitis.
Data Point: A 2018 Journal of Autoimmunity study found that male SLE patients were diagnosed 1.5 years later on average than females, partly due to lower clinical suspicion.- Age-Related Biomarker Differences Pediatric and geriatric lupus present unique diagnostic challenges:
- Pediatric SLE: Children often lack classic autoantibodies (e.g., anti-dsDNA in ~30% of cases) but may exhibit higher rates of anti-Ro/La antibodies and more severe nephritis. The 2016 EULAR/PReS criteria for juvenile idiopathic arthritis-associated lupus emphasize musculoskeletal and hematologic features over serology.
- Geriatric SLE: Older adults (>65 years) frequently present with atypical symptoms (e.g., cognitive decline, atrial fibrillation) and lower ANA titers, mimicking Alzheimer’s disease or atrial fibrillation. Only ~60% of elderly SLE patients meet ACR criteria at diagnosis.
Age-Specific Insight: The 2019 EULAR/ACR criteria include age-adjusted weighting for features like malar rash (less common in older adults) and neuropsychiatric symptoms (more prevalent in geriatric cases).Diagnostic Challenges in Pediatric Lupus
Children with lupus face distinct hurdles due to developmental differences in immune function, atypical biomarker profiles, and the need for age-specific diagnostic frameworks. Key challenges include:
- Differences in Biomarker Presentation Pediatric SLE often exhibits:
- Lower prevalence of anti-dsDNA (~30–40% vs. ~50% in adults).
- Higher frequency of anti-Ro/La antibodies (associated with neonatal lupus and congenital heart block).
- More pronounced hematologic abnormalities (e.g., hemolytic anemia, leukopenia) as initial presenting features.
Pediatric-Specific Marker: Anti-La antibodies are more common in children with lupus and may correlate with severe disease (e.g., nephritis, central nervous system involvement).- Need for Age-Adapted Diagnostic Criteria The 2016 EULAR/PReS criteria for juvenile idiopathic arthritis (JIA)-associated lupus emphasize:
- Chronic arthritis (persisting >6 weeks).
- Hematologic disorders (e.g., lymphopenia, thromb
The diagnosis of lupus demands a multidisciplinary approach that harmonizes laboratory precision with clinical acumen, ensuring that no patient falls through the cracks of overlapping symptoms or inconclusive test results. While blood-based biomarkers like ANA and anti-dsDNA antibodies remain cornerstones of diagnosis, their limitations—such as false positives in other autoimmune diseases or fluctuating levels during disease flares—highlight the need for complementary tests, including imaging and biopsies. Emerging biomarkers, though promising, await broader validation before they can reshape diagnostic paradigms, leaving clinicians to navigate current challenges with vigilance and adaptability. Ultimately, the refinement of diagnostic criteria, coupled with heightened awareness of demographic disparities and pediatric nuances, will be pivotal in bridging gaps in lupus care. This synthesis of diagnostic strategies not only clarifies the path forward for clinicians but also reinforces the imperative for continuous innovation in autoimmune disease detection.
As research advances, the integration of novel biomarkers and refined scoring systems may further enhance diagnostic accuracy, yet the foundational principles of lupus evaluation—rigorous test interpretation, symptom correlation, and interdisciplinary collaboration—will endure. The journey toward definitive lupus diagnosis is fraught with obstacles, but with a systematic and evidence-driven approach, clinicians can mitigate misdiagnoses and ensure timely, tailored interventions. The future of lupus care hinges on these diagnostic advancements, offering hope for earlier detection and improved management of this complex autoimmune condition.
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of www.linuxunplugged.com.