bmi calculator for teens essential guide
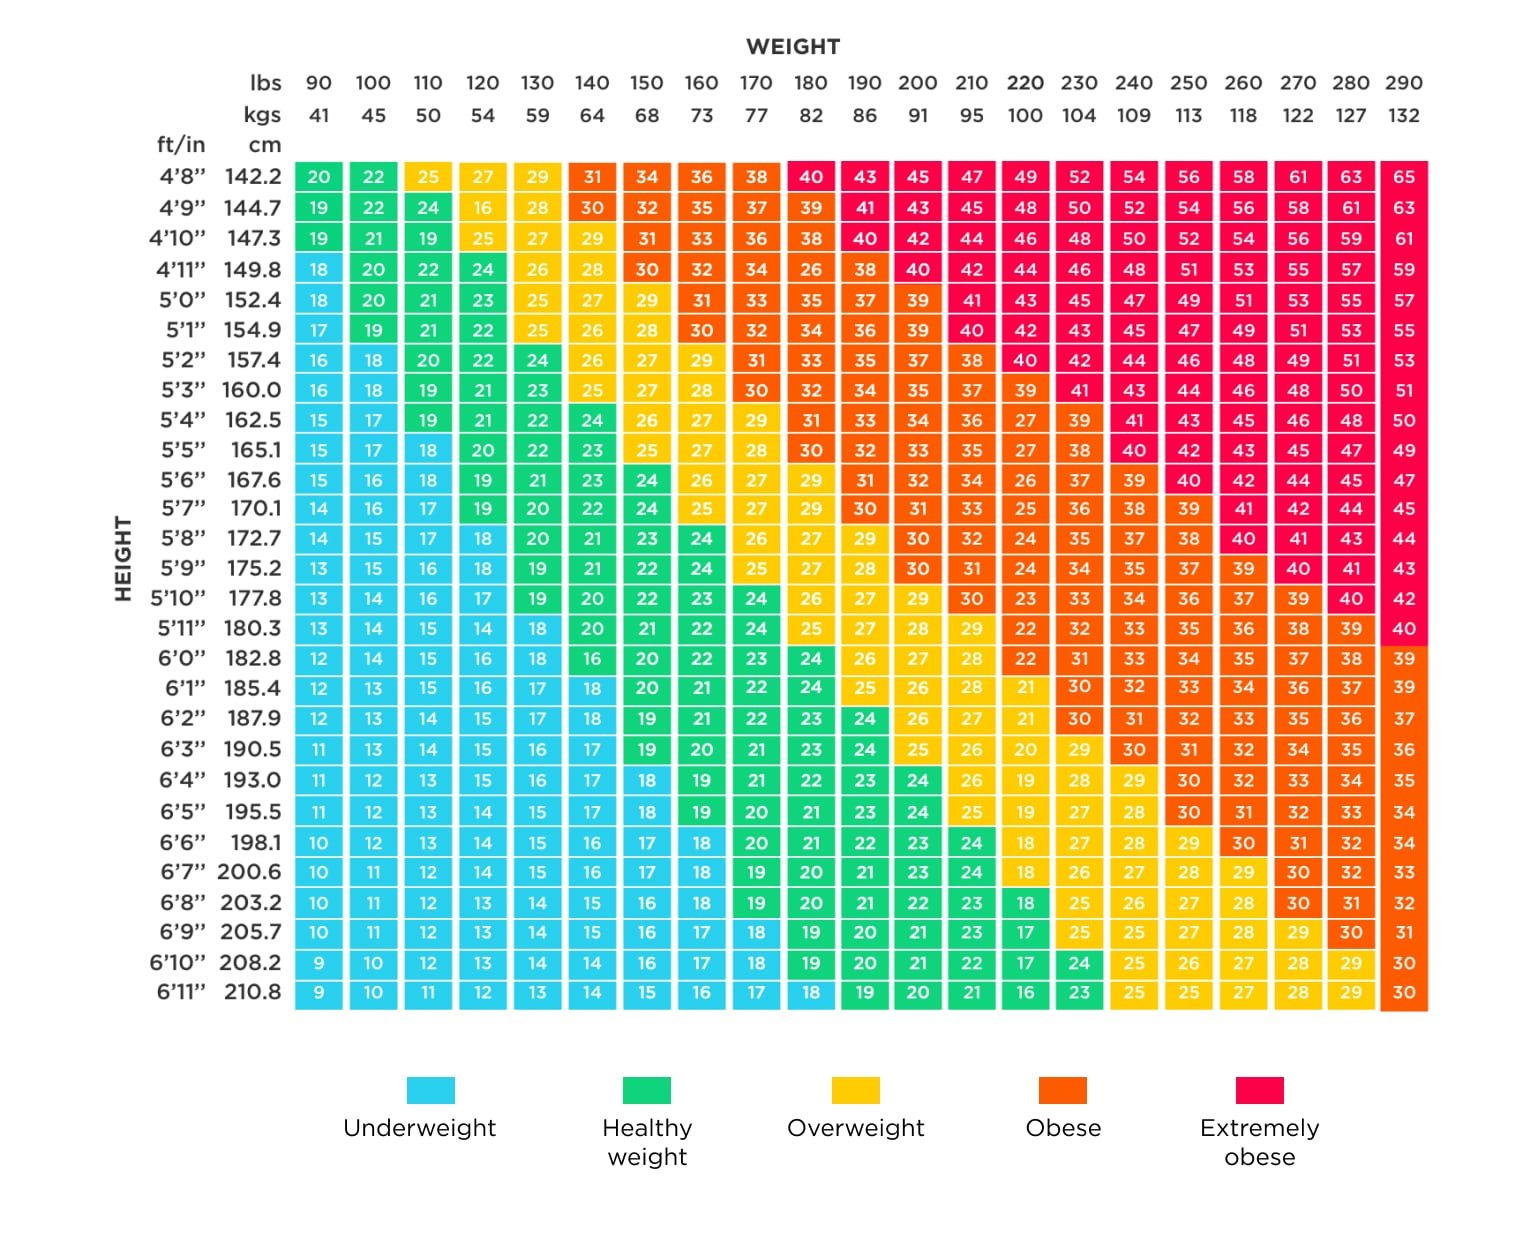
Table of Contents
- Understanding BMI for Teenagers: Foundational Concepts
- BMI Calculation Formula and Age-Specific Adjustments
- BMI Categories for Teens: CDC and WHO Benchmarks
- Comparison of BMI Calculation Methods: Teens vs. Adults
- Derivation of BMI Percentiles: Step-by-Step Process
- Practical BMI Calculator Tools for Teens
- Core Features of Teen-Focused BMI Calculators
- Comparison of Free Online BMI Calculators for Teens
- Embedding a Customizable BMI Calculator Widget
- Teen BMI Calculator
- Interpreting BMI Results: Health Implications for Teens
- Physiological and Psychological Risks by BMI Percentile Category
- Demographic Disparities in Teen BMI Trends
- Contextualizing BMI with Complementary Health Metrics
- Educational Resources and Activities for Teens
- Lesson Plan Outline for Teaching BMI to Teens
- Designing Engaging Visual Aids for BMI Education
- Discussion Prompts for Teen Group Settings
- Quiz and Self-Assessment Template for Teens
Accurate body mass index assessment is a critical component of adolescent health monitoring, yet many parents and educators struggle to navigate the nuances of BMI for teens. Unlike static adult benchmarks, teen BMI relies on dynamic percentiles adjusted for age, gender, and growth patterns, demanding a specialized approach to interpretation and application. This guide bridges the gap between clinical guidelines and practical tools, offering a structured exploration of BMI calculation methods, interpretive frameworks, and actionable resources tailored specifically for teenagers.
The transition from childhood to adulthood introduces unique physiological and psychological challenges, where BMI percentiles serve as both a diagnostic tool and a conversation starter for fostering healthy lifestyle habits. By integrating evidence-based percentiles from the CDC and WHO with user-friendly calculators and demographic insights, this resource equips stakeholders with the knowledge to contextualize BMI results within broader health trajectories. From classroom activities to digital embeddable tools, the solutions presented here ensure that BMI becomes not just a metric, but a gateway to informed decision-making for teens and their caregivers.
Understanding BMI for Teenagers: Foundational Concepts
Body Mass Index (BMI) for teenagers is a growth-based metric that accounts for variations in height, weight, and developmental stages, unlike the static thresholds used for adults. Unlike adult BMI classifications, which rely on fixed numerical ranges, pediatric BMI incorporates age- and gender-specific percentiles to reflect the dynamic nature of adolescent growth. This adjustment is critical because children and adolescents grow at different rates, and a BMI that may indicate a healthy weight for a 10-year-old could signal underweight or overweight for a 16-year-old due to differences in muscle mass, bone density, and fat distribution.The calculation of BMI for teens follows the same core formula as for adults—weight in kilograms divided by height in meters squared (kg/m²)—but the interpretation shifts from absolute values to percentiles derived from standardized growth charts. These charts, developed by the Centers for Disease Control and Prevention (CDC) and the World Health Organization (WHO), categorize BMI based on statistical distributions of large, representative populations. The use of percentiles ensures that assessments align with typical growth patterns, reducing misclassifications that could arise from applying adult BMI cutoffs to adolescents.
BMI Calculation Formula and Age-Specific Adjustments
The formula for calculating BMI remains consistent across all ages:BMI = Weight (kg) / [Height (m)]²For practical application in teens, weight should be measured in kilograms and height in meters. If measurements are taken in pounds and inches, conversions are required:
Age-specific adjustments are incorporated through growth percentiles, which account for:
Percentiles are derived from large-scale growth studies, where BMI values are ranked from lowest to highest. For instance, a 50th percentile indicates that 50% of peers of the same age and gender have a lower BMI, while a 95th percentile means only 5% have a higher BMI. This percentile-based approach ensures that BMI assessments are developmentally appropriate, avoiding false positives or negatives that could occur with rigid adult cutoffs.
BMI Categories for Teens: CDC and WHO Benchmarks
The CDC and WHO classify teen BMI using percentile thresholds rather than fixed numerical ranges. Below is a structured comparison of their frameworks, focusing on the CDC 2000 Growth Charts (most widely used in the U.S.) and the WHO 2007 Growth Standards (internationally recognized for children under 5, with extensions for older adolescents).Key Note: Percentiles are age- and gender-specific. The table below provides general categories for illustration; exact values should be cross-referenced with CDC or WHO tools for precise classification.
| Age Range | BMI Percentile (CDC 2000) | BMI Percentile (WHO 2007) | Health Risk Level |
|---|---|---|---|
| 2–19 years | <5th percentile | <3rd percentile | Underweight (may indicate malnutrition, eating disorders, or chronic illness) |
| 2–19 years | 5th–<85th percentile | 3rd–<85th percentile | Healthy weight (optimal growth and development) |
| 2–19 years | 85th–<95th percentile | 85th–<97th percentile | Overweight (increased risk of metabolic complications; monitor diet/exercise) |
| 2–19 years | >95th percentile | >97th percentile | Obese (high risk of type 2 diabetes, cardiovascular disease, and psychosocial challenges) |
Comparison of BMI Calculation Methods: Teens vs. Adults
The primary distinction between BMI calculations for teens and adults lies in the interpretation framework, not the formula itself. Below is a structured comparison highlighting why percentiles replace static ranges for adolescents:-
Static Ranges for Adults:
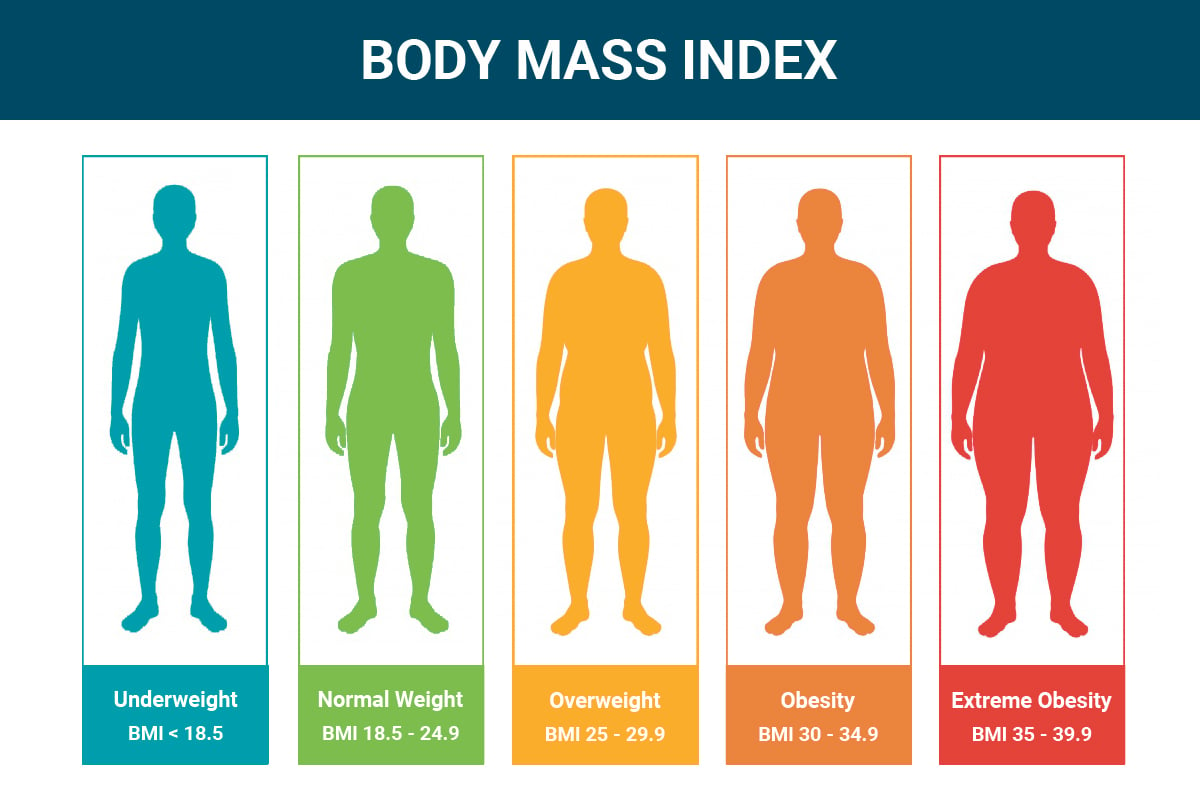
Adult BMI is classified using fixed numerical cutoffs (e.g., <18.5 = underweight, 18.5–24.9 = healthy, 25–29.9 = overweight, ≥30 = obese). These thresholds are derived from epidemiological studies linking BMI to disease risk in adult populations, where growth has plateaued.Limitations for Teens:
Applying adult cutoffs to adolescents would misclassify many as overweight or obese during normal growth phases (e.g., a 14-year-old boy with a BMI of 22 may be in the 80th percentile but would be labeled "overweight" using adult standards). -
Percentiles for Teens:
Teen BMI is assessed relative to age-, gender-, and ethnicity-specific growth curves. This accounts for:
- Muscle mass: Adolescents, particularly boys, may have higher BMIs due to increased muscle development (e.g., athletes).
- Fat distribution: Girls tend to accumulate subcutaneous fat earlier than boys, affecting BMI percentiles.
- Temporal variability: A child’s BMI percentile can fluctuate significantly over months due to growth spurts, making single-point measurements less reliable without contextual percentiles.
-
Developmental Context:
The WHO emphasizes that BMI in children should be interpreted within the "growth velocity" framework—i.e., whether the BMI percentile is stable, increasing, or decreasing over time. For example:
- A rising BMI percentile in early adolescence may reflect normal growth but warrants monitoring if it accelerates.
- A stable high percentile (e.g., 90th) may indicate a need for lifestyle interventions, whereas a stable low percentile (e.g., 10th) could signal undernutrition.
-
Clinical Actionability:
Adult BMI thresholds trigger immediate health interventions (e.g., diabetes screening at BMI ≥30). For teens, percentiles guide longitudinal monitoring rather than binary classifications. For instance:
- A teen at the 85th–94th percentile may require dietary counseling if trends suggest obesity risk.
- A teen at the 5th–10th percentile may need nutritional assessments if accompanied by symptoms like fatigue or delayed puberty.
Derivation of BMI Percentiles: Step-by-Step Process
The calculation of BMI percentiles for teens involves a multi-step process that integrates raw BMI data with growth reference datasets. Below is a textual flowchart outlining the derivation, with each step explained in detail:-
Data Collection:
Measure the teen’s weight (kg) and height (m) using standardized tools (e.g., digital scales, stadiometers). Record age in years/months and gender. For ethnic-specific charts, note the teen’s background (e.g., Hispanic, Asian).Example: A 13-year-old girl weighs
2. Hands-On Activity: Anonymous BMI Calculation (25 minutes)
Practical BMI Calculator Tools for Teens
Teen-friendly BMI calculators must balance accuracy, usability, and developmental appropriateness to ensure reliable health monitoring. These tools should accommodate varying input preferences (metric or imperial units), restrict age ranges to pediatric relevance (typically 2–20 years), and interpret results using percentile-based growth standards rather than adult BMI categories. The integration of interactive features, such as sliders or visual growth charts, enhances engagement while maintaining clinical validity, particularly for adolescents whose growth patterns differ significantly from adults.
Core Features of Teen-Focused BMI Calculators
Effective BMI calculators for teens prioritize input flexibility, age-specific normalization, and actionable output. Key functionalities include:- Unit Compatibility
Calculators must support both metric (centimeters/kilograms) and imperial (inches/pounds) measurements to accommodate global and regional preferences. Input fields should auto-validate units to prevent errors, with clear labels (e.g., "cm/ft-in") and tooltips explaining conversions.- Age and Growth Stage Restrictions
BMI interpretation for teens relies on CDC or WHO growth charts, which categorize results by age and sex (e.g., 5th–85th percentiles for "healthy weight"). Calculators should enforce an age range of 2–20 years and prompt users to select gender for accurate percentile mapping. Exclusion of adult BMI thresholds (e.g., ≥18.5 or ≥25) prevents misclassification of normal adolescent growth spurts.- Percentile-Based Results with Visual Aids
Output should display BMI percentile alongside standard classifications (e.g., "Below 5th percentile: Underweight"). Incorporating interactive growth charts—where a user’s BMI is plotted against CDC/WHO curves—provides context for trends over time. For example, a 14-year-old at the 75th percentile for weight may still be within a healthy range, whereas the same BMI in an adult would indicate overweight.- Additional Health Context
Teens benefit from supplementary features such as:
- Body Fat Estimation: Approximations (e.g., "Low/Moderate/High") using skinfold or waist-to-height ratios, where applicable.
- Activity Recommendations: Suggested physical activity minutes (e.g., 60+ per day) based on BMI percentile and age.
- Nutrition Insights: Links to balanced meal plans or calorie ranges tailored to teen metabolism.
Comparison of Free Online BMI Calculators for Teens
Selecting a calculator requires evaluating accuracy, privacy policies, and additional resources. Below is a responsive table comparing leading tools, with columns prioritizing clinical utility and user trust.
Note: For clinical use, prioritize tools aligned with CDC or WHO standards. Third-party apps may lack transparency in data sourcing or include ads targeting teens.Tool Name Accuracy Claims Data Privacy Policy Additional Features Target Audience CDC Growth Charts (CDC.gov) Uses CDC 2000 growth reference percentiles; validated for ages 2–20. Supports metric/imperial. Public domain; no user data collection. Complies with HIPAA for institutional use. - Downloadable PDF growth charts for tracking over time.
- Sex-specific and age-grouped percentiles (e.g., 2–3 yrs, 10–19 yrs).
- Educational resources on healthy growth patterns.
Healthcare providers, parents, teens (self-monitoring). NIH WeCan! BMI Calculator (nih.gov) Based on CDC data; includes waist circumference for obesity risk assessment. No personal data stored; operated by U.S. government. - Interactive "Healthy Weight" tips for teens.
- Parent/teen activity challenges (e.g., "Move Your Way").
- Links to MyPlate guidelines for calorie needs by age.
Teens 10–18 years; school wellness programs. HealthyWeight.net Teen Tool Uses WHO growth standards for global applicability; includes BMI-for-age Z-scores. Anonymized data; no tracking. Funded by non-profits. - Growth trend analyzer (plots 3+ BMI measurements).
- Multilingual interface (English/Spanish/French).
- Screening for disordered eating behaviors.
Diverse populations; teens in non-U.S. regions. MyFitnessPal Teen BMI Tracker Third-party integration with CDC data; less precise for under-5s. Data shared with parent accounts if linked; opt-out available. - Syncs with fitness apps (e.g., Fitbit) for activity correlation.
- Meal logging with teen-friendly portion sizes.
- Social sharing (optional) for accountability.
Tech-savvy teens; those using fitness trackers.
Embedding a Customizable BMI Calculator Widget
Integrating a BMI calculator into a teen health blog or school portal requires HTML/JavaScript with considerations for responsiveness, accessibility, and data security. Below are step-by-step instructions for a basic, self-hosted widget using vanilla JavaScript.### Step 1: HTML Structure
Create a container with input fields for height, weight, age, and gender. Include a submit button and result display area.Teen BMI Calculator
Your BMI Percentile:
Category:
### Step 2: JavaScript Logic
Use the CDC BMI-for-age percentile formula (or WHO for global use) to compute results. Validate inputs and restrict age/gender selections.document.getElementById('bmiForm').addEventListener('submit', function(e) {
e.preventDefault();
const height = parseFloat(document.getElementById('height').value);
const weight = parseFloat(document.getElementById('weight').value);
const
Interpreting BMI Results: Health Implications for Teens
Body Mass Index (BMI) in adolescents serves as a critical screening tool to assess weight status relative to height, but its interpretation requires nuanced understanding of developmental stages, physiological risks, and demographic variations. While BMI percentiles provide a standardized framework, they must be evaluated alongside clinical indicators to derive meaningful health insights. This section explores the physiological and psychological risks associated with each BMI category, demographic disparities in BMI trends, and the necessity of contextualizing results with complementary health metrics.
Physiological and Psychological Risks by BMI Percentile Category
BMI percentiles for teens are categorized as follows: underweight (<5th percentile), healthy weight (5th–<85th percentile), overweight (85th–<95th percentile), and obese (≥95th percentile). Each category carries distinct health risks, influenced by age, pubertal stage, and genetic predispositions.Underweight Teens (<5th Percentile)
Underweight status in adolescents may reflect chronic undernutrition, metabolic disorders, or psychological factors such as eating disorders. Key risks include:
- Growth stunting and delayed puberty: Chronic caloric deficiency impairs linear growth and hormonal development, particularly in early adolescence (CDC, 2021).
- Weakened immune function: Lower BMI correlates with increased susceptibility to infections, slower wound healing, and reduced bone density (WHO, 2020).
- Psychological distress: Stigmatization or self-perceived "thinness" may contribute to anxiety or disordered eating patterns, though underweight teens are less likely to report body dissatisfaction than overweight peers (APA, 2019).
- Metabolic adaptations: Some underweight teens exhibit slowed basal metabolic rates, exacerbating energy deficits (NIH, 2022).
Overweight Teens (85th–<95th Percentile)
Early signs of excess adiposity in adolescence often precede metabolic syndrome and cardiovascular disease. Risks include:
- Insulin resistance and prediabetes: Overweight teens show elevated fasting glucose levels, with 15–20% meeting prediabetes criteria (ADA, 2021).
- Orthopedic stress: Excess weight accelerates joint degeneration, increasing risks of slipped capital femoral epiphysis (SCFE) and flatfoot deformities (American Academy of Pediatrics, 2020).
- Sleep apnea and respiratory complications: Obstructive sleep apnea (OSA) prevalence rises to 10–15% in overweight teens, linked to daytime fatigue and cognitive impairments (AASM, 2021).
- Psychosocial challenges: Stigma-related bullying and internalized weight bias contribute to depression and lower self-esteem, with overweight girls showing higher rates of depressive symptoms (CDC, 2022).
Obese Teens (≥95th Percentile)
Obesity in adolescence is associated with severe, often irreversible health consequences if unaddressed. Critical risks include:
- Metabolic syndrome: Clustered risks (hypertension, dyslipidemia, hyperglycemia) affect 30–40% of obese teens, with a 70% likelihood of persisting into adulthood (NHANES, 2020).
- Non-alcoholic fatty liver disease (NAFLD): Prevalence reaches 10–15% in obese teens, progressing to cirrhosis in 5–10% of cases (AASLD, 2021).
- Mental health disorders: Obese teens face a 2–3x higher risk of anxiety and major depressive disorder, partially mediated by social exclusion (NIMH, 2022).
- Premature cardiovascular disease: Elevated LDL cholesterol and blood pressure in obese teens predict atherosclerosis by age 30 (Framingham Heart Study, 2021).
Blockquote: Clinical Red Flags for Obese Teens
> "Persistent BMI ≥95th percentile beyond age 12, combined with acanthosis nigricans (darkened neck skin), elevated triglycerides (>150 mg/dL), or family history of type 2 diabetes, warrants immediate pediatric endocrinology referral." — Endocrine Society Clinical Practice Guidelines (2020)
Demographic Disparities in Teen BMI Trends
BMI distributions vary significantly across socioeconomic status (SES), ethnicity, and geographic regions, reflecting systemic health inequities. Below is a comparative analysis of obesity prevalence (BMI ≥95th percentile) among U.S. teens (ages 12–19) based on 2022 CDC data:
Note: Ethnic disparities in BMI are influenced by genetic ancestry, cultural dietary practices, and environmental factors. For example, South Asian teens may exhibit obesity-related risks (e.g., cardiovascular disease) at lower BMIs than European descent peers (WHO, 2020).Demographic Group Obesity Prevalence (%) Key Risk Factors Data Source Hispanic Teens 22.5% - Higher rates of food insecurity (30% vs. 12% in non-Hispanic whites) (USDA, 2021).
- Cultural norms favoring larger body sizes and limited access to fresh produce in low-income neighborhoods.
- Genetic predisposition to insulin resistance (e.g., higher prevalence of PCOS in Hispanic girls).
CDC National Health and Nutrition Examination Survey (NHANES), 2022 Non-Hispanic Black Teens 20.8% - Systemic racism-linked stress elevates cortisol levels, promoting visceral fat accumulation (APA, 2020).
- Higher exposure to fast-food advertising (30% more TV ads targeting Black youth) (RWJF, 2021).
- Delayed puberty in girls, increasing obesity risk during adolescent growth spurts.
CDC, 2022 Non-Hispanic White Teens 16.2% - Lower food insecurity but higher rates of disordered eating (e.g., restrictive diets) (NEDA, 2021).
- Overrepresentation in "obesogenic" environments (e.g., rural areas with limited walkable spaces).
CDC, 2022 Asian Teens 9.5% - BMI thresholds for obesity may underestimate risk due to higher visceral fat at lower BMIs (WHO Asia-Pacific Guidelines, 2020).
- Dietary patterns (e.g., high sodium, low fiber) contribute to hypertension and metabolic syndrome.
CDC, 2022 (Note: Asian teens often classified under "other" in NHANES) Low-Income Teens (Household Income <185% FPL) 24.1% - Limited access to supermarkets ("food deserts" affect 1 in 5 low-income teens) (USDA, 2021).
- Reliance on energy-dense, low-nutrient foods (e.g., 40% higher soda consumption vs. higher-income peers) (Harvard T.H. Chan School, 2022).
CDC, 2022
Contextualizing BMI with Complementary Health Metrics
BMI alone does not capture body composition, fat distribution, or metabolic health. Pediatricians and teens should monitor the following complementary metrics to refine health assessments:- Waist Circumference (WC):
- Cutoffs for teens: ≥90th percentile for age/sex (e.g., ≥35 inches for girls, ≥38 inches for boys at age 15) (NIH, 2021).
- Risk:
Educational Resources and Activities for Teens
Understanding Body Mass Index (BMI) among teenagers requires an interactive and engaging approach that balances theoretical knowledge with practical application. Educational resources and hands-on activities help teens grasp BMI concepts while fostering critical thinking about health, body image, and cultural influences. This section provides structured lesson plans, visual aids, discussion prompts, and self-assessment tools tailored to teen audiences, ensuring ethical participation and accurate health literacy.
Lesson Plan Outline for Teaching BMI to Teens
A structured lesson plan ensures teens comprehend BMI’s relevance to their health while addressing misconceptions. The outline below integrates theoretical explanations, group activities, and reflective discussions, adhering to ethical guidelines for anonymity, consent, and privacy.Lesson Duration: 60–90 minutes
Group Size: 10–30 teens (adjustable for smaller/large classes)
Materials Required:
- Measuring tapes, height rods, or digital scales (for anonymous measurements)
- Printed BMI-for-age percentile charts (CDC or WHO growth standards)
- Whiteboard or digital presentation tool
- Worksheets for calculations and reflections
Lesson Structure:
1. Introduction to BMI (15 minutes)
- Define BMI as a screening tool for body fatness, emphasizing its limitations (e.g., muscle mass, bone density).
- Present a growth chart infographic comparing BMI percentiles across ages 2–20, using color gradients (green for healthy, yellow for at risk, red for high risk).
- Key Formula:
BMI = (Weight in kg) / (Height in meters)²
Percentile = Position of BMI value on age/gender-specific CDC growth charts.
- Ethical Guidelines:
- Teens provide measurements voluntarily; no names or identifiable data are recorded.
- Results are shared only as group percentiles (e.g., "5 students fall in the 85th–94th percentile").
- Focus on trends, not individual comparisons.
- Procedure:
- Measure heights (standing against a wall or using a stadiometer) and weights (digital scale) in pairs.
- Calculate BMI using the formula, then plot results on percentile charts.
- Discuss patterns (e.g., "Why might some teens in the same age group have widely varying BMIs?").
- Use prompts to explore perceptions of BMI, such as:
- The impact of social media or peer pressure on body image.
- Cultural norms around weight (e.g., athletic vs. sedentary lifestyles).
- Misconceptions about BMI (e.g., "A high BMI always means poor health").
- Visual Aid: Display side-by-side images of athletes (e.g., football players vs. marathon runners) with similar BMIs but different body compositions.
- Teens complete a worksheet with:
- One takeaway from the activity.
- A realistic goal for maintaining a healthy BMI (e.g., "Increase vegetable intake by 1 serving/day").
- Distribute a fact sheet on balanced nutrition and physical activity tailored to teens.
- Color-Coded Ranges:
- Use a traffic-light gradient (green: 5th–84th percentile [healthy], yellow: 85th–94th [at risk], red: ≥95th [high risk]).
- Example: A bar graph where each teen’s BMI percentile is marked with a colored dot on a class-wide chart.
- Dynamic Elements:
- Include sliders (e.g., "Drag to adjust height/weight and see BMI change") in digital tools.
- Animate percentile shifts over time (e.g., "How does BMI change from age 10 to 16?").
- Common Myths Debunked:
- Myth: "All high BMIs mean obesity." Visual: Side-by-side images of a muscular teen and a sedentary teen with the same BMI, labeled "Body composition matters."
- Myth: "BMI is the same for adults and teens." Visual: Overlay CDC growth charts for ages 2–20 vs. adult BMI categories, highlighting percentile differences.
- Design Tips:
- Use icons (e.g., 🍎 for nutrition, 🏃 for activity) to break down healthy habits.
- Include real teen testimonials (e.g., "I thought my BMI was ‘bad’ until I learned about muscle mass").
- Self-Comparison Feature:
- Teens input their stats to see their percentile, then compare to fictional characters (e.g., "Your BMI is like [Character X]’s").
- Trend Tracker:
- A line graph showing BMI percentiles from age 10–18, with notes on growth spurts or lifestyle changes.
- Prompt: "How do movies, social media, or sports culture shape what teens consider a ‘healthy’ BMI?"
- Follow-Up: Show clips from films or ads depicting unrealistic body standards, then ask, "How might these affect self-perception?"
- Example Activity: Teens create a collage of images representing "healthy bodies" vs. "unhealthy bodies" and discuss discrepancies.
- Prompt: "What are sustainable ways to improve BMI without extreme diets or excessive exercise?"
- Key Points to Highlight:
- Nutrition: "Adding one fruit/vegetable serving daily" vs. "cutting out all carbs."
- Activity: "Walking 10 minutes after meals" vs. "marathons."
- Visual Aid: A Venn diagram comparing "fad diets" and "balanced eating" with teen-approved foods (e.g., pizza vs. salads).
- Prompt: "Why might BMI not tell the whole story about a teen’s health?"
- Discussion Points:
- Muscle mass (e.g., wrestlers vs. swimmers).
- Ethnicity (e.g., Asian teens may have higher health risks at lower BMIs).
- Activity: Teens research and present alternative health metrics (e.g., waist-to-height ratio, fitness tests).
- Prompt: "How can friends help each other maintain healthy habits without judgment?"
- Role-Play Scenario: Teens practice giving constructive feedback (e.g., "Want to try the salad bar with me?" vs. "You’re eating too much").
3. Group Discussion: Health and Cultural Context (20 minutes)
4. Reflection and Action Plan (20 minutes)
Designing Engaging Visual Aids for BMI Education
Visual aids simplify complex data and make BMI concepts memorable for teens. Effective designs use color, interactivity, and relatable examples. Below are key principles for creating growth charts, infographics, and interactive tools.1. Growth Charts and Percentile Tools
2. Infographics for Misconceptions
3. Interactive Digital Tools
Discussion Prompts for Teen Group Settings
Guided discussions encourage teens to reflect critically on BMI, health, and societal influences. Prompts should be open-ended, culturally sensitive, and avoid shaming. Below are evidence-based topics with discussion starters.1. Body Image and Cultural Norms
2. Healthy Lifestyle Adjustments
3. BMI Limitations and Alternatives
4. Peer Support and Accountability
Quiz and Self-Assessment Template for Teens
Self-assessment tools reinforce learning and identify knowledge gaps. Below is a checklist-style quiz and a table-based template for teens to evaluate their understanding of BMI. Questions align with CDC guidelines and common teen misconceptions.Quiz: True/False and Short-Answer Questions
1. True/False: A teen with a BMI in the 95th percentile is automatically classified as obese.Self-Assessment Table: Evaluating BMI Knowledge
(False: Obesity requires clinical evaluation beyond BMI.) 2. True/False: BMI accounts for differences in muscle mass.
(False: BMI does not distinguish muscle from fat.) 3. Short Answer: Name two factors that can affect a teen’s BMI percentile besides diet.
(Answers: Growth spurts, genetics, physical activity level.) 4. Scenario: A 14-year-old male weighs 120 lbs and is 5’6”. His BMI is 22. What percentile range is this likely in?
(Answer: Healthy range [5th–84th percentile], assuming average growth.) 5. Discussion Question: Why might a teen with a high BMI still have good cardiovascular health?
(Answer: Factors like diet quality, activity level, or family history play a role.)
| Topic | I Understand | I Need to Learn More | Notes |
|---|---|---|---|
| How to calculate BMI | ☐ Yes / ☐ No | ☐ | |
| BMI percentile ranges | ☐ Yes / ☐ No | ☐ | (e |
Understanding BMI in teens is more than a numerical exercise—it is a foundation for lifelong health literacy. By mastering percentile-based calculations, leveraging interactive tools, and contextualizing results with complementary health markers, educators, parents, and adolescents can transform BMI data into meaningful action. The resources outlined here—from lesson plans to customizable calculators—demonstrate that health education need not be clinical or intimidating. Instead, it can be collaborative, visually engaging, and empowering, ensuring that every teen has the clarity and confidence to navigate their growth journey with informed optimism.
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of www.linuxunplugged.com.