bmi calculator child essentials methodology applications
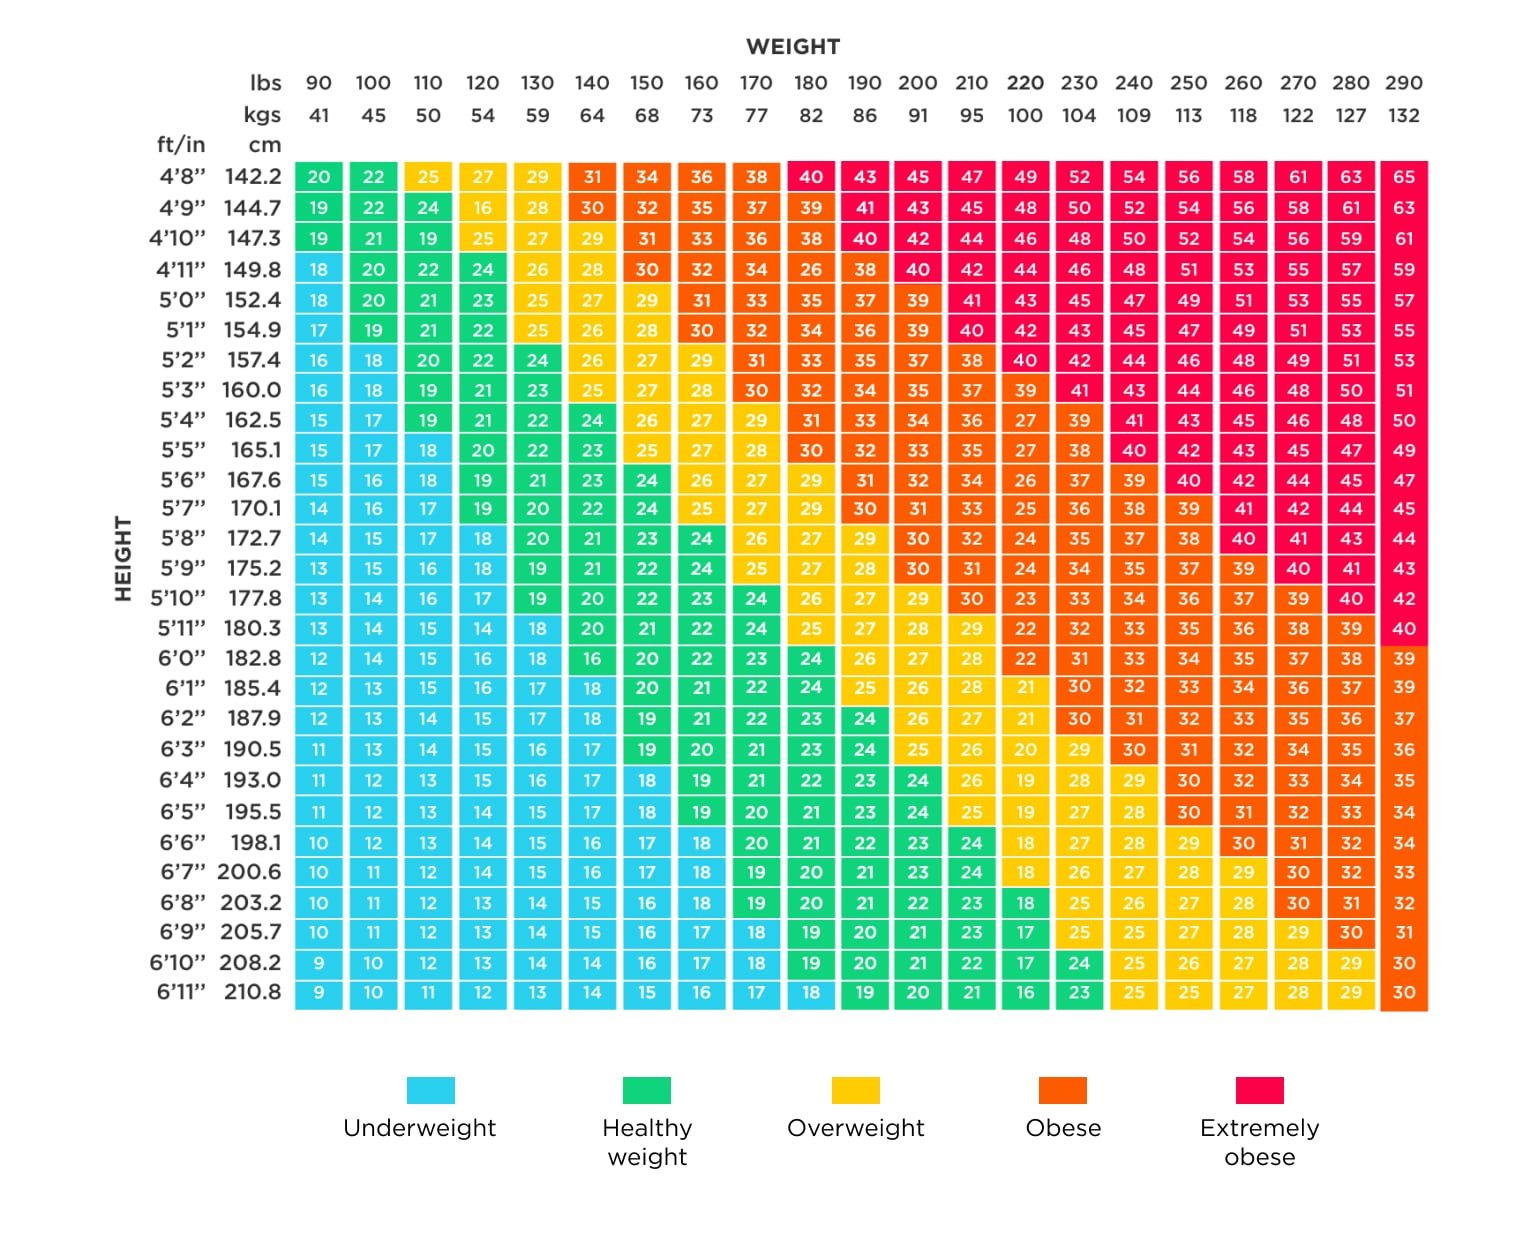
Table of Contents
- Understanding BMI for Children: Core Concepts and Methodology
- Differences Between Adult and Child BMI Calculations
- CDC Growth Charts and Weight Status Categories
- Step-by-Step Manual Calculation of Child BMI and Percentile Conversion
- BMI Percentile Comparison for Boys and Girls at Key Ages
- Technical Development: Building a Functional BMI Calculator for Children
- Algorithms for BMI Percentile Calculation
- Load LMS parameters for given age and gender (simplified)
- Web-Based Calculator Structure and Input Validation
- Essential UI/UX Features for Child-Friendly Design
- Educational Applications: Teaching Tools and Interactive Features for Child BMI Awareness
- Interactive Quiz: Drag-and-Drop BMI Percentile Matching Activity
- Infographic: Visualizing BMI Percentile Changes Across Childhood Growth Stages
- Integrating BMI Calculators into School Health Programs
- Presenting BMI Data in Child Health Report Cards
- Health Implications: Interpreting BMI Results for Parents and Caregivers
- Limitations of BMI as a Sole Health Indicator
- Red Flags in BMI Trends and Pediatric Consultation Steps
- Framing BMI Discussions with Children to Avoid Stigma
- Parent Guide: Using BMI Data to Set Realistic Health Goals
- Comparative Analysis of BMI Calculators for Children Across Platforms and Demographics
- Methodological Differences in BMI Calculation for Children
- Demographic Gaps in Existing BMI Calculators
- Survey Template for Parental Feedback on BMI Calculator Usability
- Adapting BMI Calculators for Diverse Populations
Accurate assessment of childhood growth through BMI percentiles remains a cornerstone of pediatric health monitoring, yet its application demands precision tailored to developmental stages. Unlike adult BMI metrics, child calculations integrate age, gender, and CDC growth charts to classify weight status—ranging from underweight to obesity—while accounting for natural variability in growth patterns. This framework not only informs clinical decisions but also serves as an educational tool for parents and educators to foster healthy habits early. Below, we explore the technical, pedagogical, and health-related dimensions of designing a functional BMI calculator for children aged 2 to 20.
The process begins with a rigorous methodology that distinguishes child BMI from adult standards, emphasizing percentile-based interpretations over fixed thresholds. By leveraging CDC reference tables, practitioners and developers can translate raw height and weight inputs into actionable health insights, complete with visual aids like growth charts and progress bars. Beyond calculation, the tool’s design must prioritize clarity, accessibility, and cultural relevance to ensure equitable application across diverse populations. This discussion bridges technical implementation with real-world educational and health applications, addressing both the science and the human-centered aspects of child BMI assessment.
Understanding BMI for Children: Core Concepts and Methodology
Body Mass Index (BMI) for children differs fundamentally from adult BMI calculations due to developmental variations in growth patterns, body composition, and fat distribution. Unlike static adult thresholds, pediatric BMI is interpreted using percentile-based rankings derived from age- and gender-specific growth charts, as established by the Centers for Disease Control and Prevention (CDC). These charts account for the natural progression of height and weight across childhood and adolescence, ensuring accurate classification of weight status relative to peers rather than fixed numerical cutoffs. The CDC methodology employs LMS (Lambda-Mu-Sigma) smoothing techniques to model BMI distributions, which adjust for the nonlinear relationship between age, height, and weight.
The primary distinction lies in the absence of universal BMI categories for children. Instead, BMI percentiles are categorized into four weight status groups—underweight, healthy weight, overweight, and obesity—based on CDC-defined thresholds that vary by age and gender. This approach acknowledges that children grow at different rates, and a BMI in the 85th percentile for a 5-year-old may reflect a different health implication than the same percentile for a 15-year-old. Below, the methodology for manual calculation and percentile interpretation is detailed, alongside a comparative analysis of CDC growth chart thresholds.
Differences Between Adult and Child BMI Calculations
Adult BMI calculations use a fixed formula (weight in kilograms divided by height in meters squared) with static thresholds (e.g., underweight <18.5, healthy 18.5–24.9, overweight 25.0–29.9, obesity ≥30.0). In contrast, pediatric BMI incorporates age- and gender-specific adjustments due to:The CDC growth charts (2000) provide separate curves for boys and girls aged 2–20 years, with BMI percentiles ranging from <5th to ≥95th. These curves are derived from national health examination data, ensuring representativeness across diverse populations. For children under 2 years, the World Health Organization (WHO) growth standards are used due to distinct early developmental patterns.
CDC Growth Charts and Weight Status Categories
The CDC defines weight status categories for children aged 2–20 years using BMI percentiles, as follows:| Weight Status | BMI Percentile Range | Health Implications |
|---|---|---|
| Underweight | <5th percentile | Potential nutritional deficiencies, delayed growth, or metabolic disorders. |
| Healthy Weight | 5th to <85th percentile | Optimal growth and development; minimal health risks. |
| Overweight | 85th to <95th percentile | Increased risk of cardiovascular disease, type 2 diabetes, and joint stress. |
| Obesity | ≥95th percentile | High likelihood of comorbidities (e.g., hypertension, fatty liver), requiring intervention. |
Step-by-Step Manual Calculation of Child BMI and Percentile Conversion
To manually calculate a child’s BMI and determine its percentile rank using CDC growth charts:1. Gather Inputs
2. Convert Height to Meters
Divide height by 100 to convert to meters:
120 cm ÷ 100 = 1.20 m
3. Calculate BMI
Use the formula:
BMI = weight (kg) / [height (m)]²
Example: 30 kg / (1.20 m)² = 30 / 1.44 = 20.83 kg/m²
4. Locate Age- and Gender-Specific CDC Percentile
5. Determine Weight Status
Compare the percentile to CDC thresholds:
Example Workflow:
For a 10-year-old girl weighing 45 kg and 145 cm tall:
BMI Percentile Comparison for Boys and Girls at Key Ages
The following table compares BMI thresholds for underweight, healthy weight, overweight, and obesity at ages 5, 10, and 15 for boys and girls, based on CDC growth charts. Values are approximate and should be cross-referenced with official charts for precision.| Age | Gender | Underweight (<5th) | Healthy Weight (5th–85th) | Overweight (85th–95th) | Obesity (≥95th) | |||||||||||||||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 5 years | Boys | <13.5 kg/m² | 13.5–17.5 kg/m² | 17.6–18.5 kg/m² | >18.5 kg/m² | |||||||||||||||||||||||||||||||||||||||||
| Girls | <13.0 kg/m² | 13.0–17.0 kg/m² | 17.1–18.0 kg/m² | >18.0 kg/m² | ||||||||||||||||||||||||||||||||||||||||||
| 10 years | Boys | <14.0 kg/m² | 14.0–19.0 kg/m² | 19.1–20.5 kg/m² | >20.5 kg/m² | |||||||||||||||||||||||||||||||||||||||||
| Girls | <13.5 kg/m² | 13.5–18.5 kg/m² | 18.6–20.0 kg/m² | >20.0 kg/m² | ||||||||||||||||||||||||||||||||||||||||||
| 15 years | Boys | <17.0 kg/m² | 17.0–24.0 kg/m² | 24.1–26.0 kg/m² | >26.0 kg/m² | |||||||||||||||||||||||||||||||||||||||||
| Age Group | Sample Tip | Example |
|---|---|---|
| 3–5 Years | Encourage play-based activity | "Try 30 minutes of outdoor play daily—like riding a bike or dancing!" |
| 6–8 Years | Balance screen time with movement | "Swap 30 minutes of TV for a walk or sports practice after school." |
| 9–12 Years | Involve in meal planning | "Ask your child to pick one new vegetable to try each week." |
Example Report Card Excerpt:
"Your child’s BMI is currently at the 85th percentile for their age and height. This means they are in the ‘healthy weight’ range, but we recommend increasing water intake and reducing sugary drinks. Here’s a fun challenge: Try adding a piece of fruit to every snack!"
Health Implications: Interpreting BMI Results for Parents and Caregivers
BMI is a widely used screening tool to assess weight status in children, but its interpretation requires nuance to avoid misclassification or unnecessary concern. While BMI percentiles provide a general framework for evaluating growth patterns, they do not account for individual variations in body composition, such as muscle mass, bone density, or ethnic differences in fat distribution. Parents and caregivers must approach BMI data as one component of a broader health assessment, integrating clinical judgment, family history, and developmental milestones to ensure accurate and actionable insights.BMI percentiles are age- and sex-specific tools designed to track growth trends over time, not to diagnose health conditions. A single measurement outside typical ranges warrants further evaluation, not immediate intervention.
Limitations of BMI as a Sole Health Indicator
BMI is derived from height and weight, making it an imperfect proxy for body fatness, particularly in children. Key limitations include:- Muscle Mass and Athletic Build: Children engaged in strength training, sports, or physically active lifestyles may exhibit higher BMI percentiles due to increased muscle mass, which does not correlate with adverse health risks. For example, a 10-year-old soccer player with a BMI in the 90th percentile may have low body fat but appear overweight based solely on BMI.
Recommendation: BMI should be interpreted in the context of:
Red Flags in BMI Trends and Pediatric Consultation Steps
Abnormal BMI trends—whether upward or downward—may signal underlying health concerns requiring professional evaluation. Below is a table outlining key red flags and corresponding actions for parents and caregivers.| Red Flag | Possible Causes | When to Consult a Pediatrician | Recommended Next Steps |
|---|---|---|---|
| Rapid weight gain (>1 BMI percentile per year) in a short period (e.g., 3–6 months) |
|
If sustained for ≥6 months or accompanied by fatigue, sleep apnea, or joint pain. |
|
| Rapid weight loss (>1 BMI percentile drop) without intentional changes |
|
If accompanied by lethargy, abdominal pain, or changes in appetite. |
|
| BMI percentile crossing ≥2 major percentiles (e.g., from 50th to 85th) in 1 year |
|
If the child shows signs of metabolic syndrome (e.g., acanthosis nigricans, high blood pressure). |
|
| Consistently low BMI (<5th percentile) with poor growth or developmental delays |
|
If the child exhibits stunted growth, frequent infections, or delayed puberty. |
|
Framing BMI Discussions with Children to Avoid Stigma
Conversations about BMI should prioritize growth, health, and empowerment over criticism or labeling. Children are highly sensitive to language that implies judgment, which can lead to body dissatisfaction, disordered eating, or avoidance of physical activity. The following strategies promote positive dialogue:- Focus on Health Behaviors, Not Numbers:
Replace statements like "Your BMI is high" with:
"Let’s think about how we can add more fruits and veggies to your meals to help your body grow strong!"
Emphasize activity levels, sleep quality, and nutrient density as markers of well-being.
- Use Strength-Based Language:
Highlight attributes unrelated to weight, such as:
"You’re so energetic during soccer practice—that’s a sign of a healthy, active body!"
Avoid phrases like "You’re getting bigger" or "You need to lose weight," which can trigger shame.
- Involve the Child in Goal Setting:
Frame discussions as collaborative experiments rather than directives:
"What’s one new vegetable you’d like to try this week? Let’s pick a fun recipe together!"
Use SMART goals (Specific, Measurable, Achievable, Relevant, Time-bound) tailored to their interests (e.g., "Can you help me find a 10-minute dance video to do after dinner?").
- Normalize Growth Variations:
Explain that bodies change at different rates:
"Some kids grow taller faster than others, and that’s okay! What matters is that you’re healthy and happy."
Share examples of diverse body types in media or sports (e.g., basketball players, dancers) to broaden perspectives.
- Avoid Public or Comparative Language:
Never discuss BMI or weight in front of peers or compare children to siblings/friends. Instead, use private, one-on-one conversations with a neutral tone:
"I noticed you’ve been really into swimming lately—that’s awesome! How do you feel about your body after practice?"
Parent Guide: Using BMI Data to Set Realistic Health Goals
This template provides a structured approach for parents to translate BMI data into actionable, age-appropriate goals. The guide is divided by developmental stages to align with cognitive and physical capabilities.Template for Parent Guide
Title: *N
Comparative Analysis of BMI Calculators for Children Across Platforms and Demographics
BMI calculators for children vary significantly in methodology, data sources, and applicability to diverse populations. While widely used tools such as those developed by the Centers for Disease Control and Prevention (CDC) and National Health Service (NHS) provide evidence-based percentile rankings, private apps and commercial platforms often employ proprietary algorithms that may lack transparency or validation. These discrepancies raise critical questions about accuracy, particularly when assessing children from non-Western ethnicities, those with medical conditions, or developmental disabilities. A systematic comparison of these tools reveals inconsistencies in growth charts, percentile adjustments, and cultural considerations, necessitating a structured evaluation to identify gaps and improve accessibility.
The following analysis examines the methodological differences among leading BMI calculators, highlights demographic limitations, and proposes adaptations to enhance inclusivity. Additionally, a survey template is provided to gather parental feedback on usability, ensuring tools align with real-world needs.
Methodological Differences in BMI Calculation for Children
BMI calculators for children primarily rely on age- and sex-specific growth charts to classify weight status into percentiles (e.g., underweight, healthy weight, overweight, obese). However, the underlying data sources and statistical models differ across platforms, leading to variations in percentile thresholds and interpretations.Key methodological distinctions include:
- Percentile Calculation Methods:
Example of Discrepancy:
A 10-year-old child with a BMI of 18.5 kg/m² may be classified as "healthy weight" in CDC charts (50th–85th percentile) but "underweight" in WHO standards (below 5th percentile for some ethnic groups). This variation underscores the need for context-specific tools.
Demographic Gaps in Existing BMI Calculators
Most BMI calculators are designed based on Westernized growth patterns, leading to systemic biases for children from non-European descent, those with disabilities, or unique medical conditions. The following populations face significant limitations:- Ethnic and Racial Diversity:
- Children with Disabilities:
- Cultural and Dietary Considerations:
Table: Key Limitations by Demographic Group
| Demographic Group | Gap in Current Calculators | Proposed Solution |
|---|---|---|
| Non-Western Ethnicities | Over/underestimation due to ethnic-specific BMI trends | Integrate IOTF or country-specific growth charts |
| Children with Disabilities | Ignores body composition differences | Use FFMI or condition-specific percentiles |
| Preterm/Low Birthweight | WHO charts limited to <2 years | Extend preterm-adjusted charts beyond infancy |
| Refugee/Migrant Children | Lack of data on rapid growth post-migration | Collaborate with pediatric nutritionists for local data |
Survey Template for Parental Feedback on BMI Calculator Usability
To assess the practicality and trustworthiness of BMI calculators, a structured survey should target parents/caregivers of children aged 0–18 years, segmented by age groups (toddlers, school-age, teens). The survey should evaluate clarity, accuracy perceptions, and barriers to use, with questions tailored to specific needs.Survey Structure:
1. Demographic Filtering:
2. Usability Questions (Likert Scale 1–5):
3. Platform-Specific Feedback:
4. Age-Group-Specific Questions:
Example Question for Cultural Adaptability:
Data Analysis Focus:
Adapting BMI Calculators for Diverse Populations
To improve inclusivity, BMI calculators must incorporate ethnicity-specific adjustments, medical condition modifiers, and cultural context. The following strategies ensure accuracy and relevance:- Ethnic-Specific Percentile Adjustments:
- Medical Condition Modifiers:
- Cultural and Dietary Context:
Effective child BMI assessment transcends mere numerical calculation, requiring a multifaceted approach that integrates technical accuracy, educational engagement, and sensitive communication. From algorithmic precision in percentile determination to user-friendly interfaces that demystify growth trends for parents and children alike, the tool must serve as both a diagnostic instrument and a catalyst for proactive health behaviors. By addressing limitations—such as muscle mass biases or cultural dietary nuances—and adapting to diverse demographics, BMI calculators can evolve into indispensable resources in pediatric care. Ultimately, the goal extends beyond data interpretation to empowering families with actionable, stigma-free strategies for nurturing lifelong wellness.
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of www.linuxunplugged.com.